Salvage EUS-guided choledochoduodenostomy after failed ERCP
The video requires an internet connection.
History
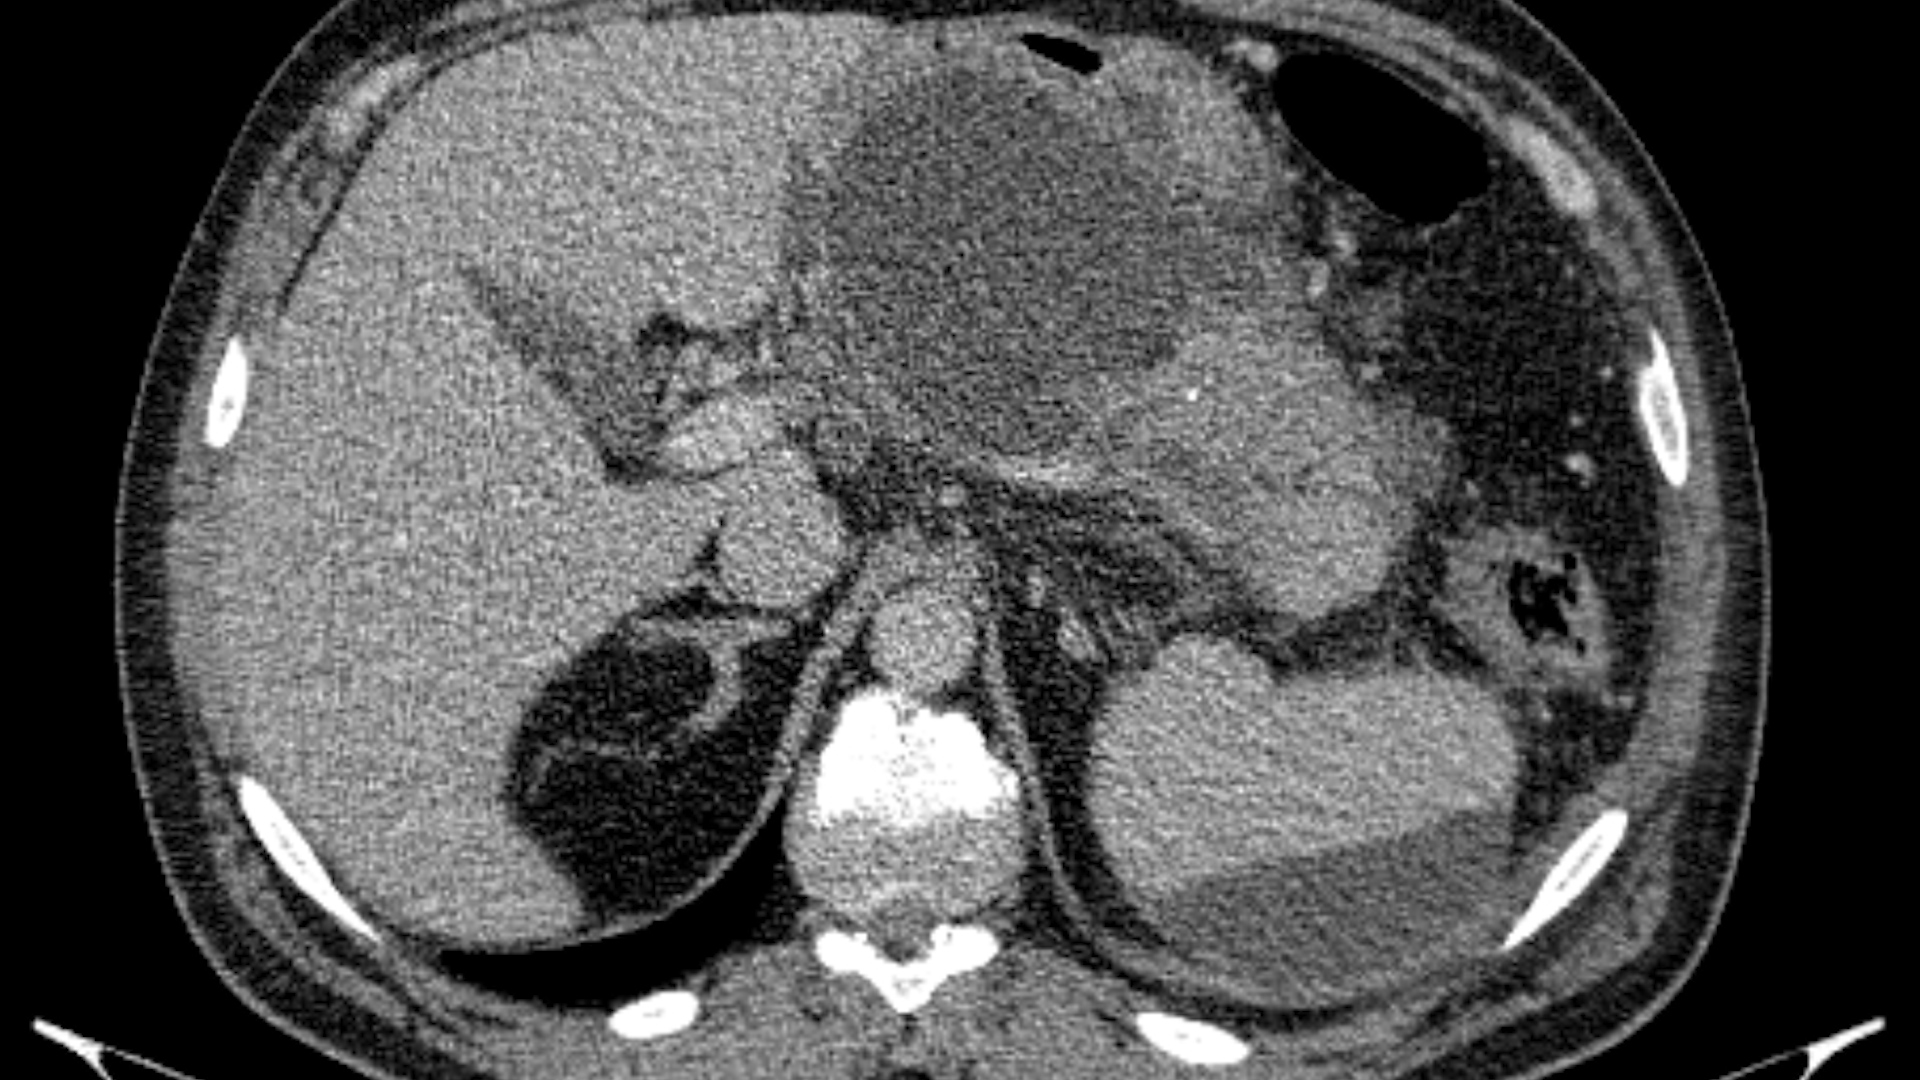
A 76-year-old obese female patient (BMI 38.8 kg/m²) was referred for progressive obstructive jaundice. Work-up identified a distal biliary stricture with severe upstream cholestasis. Because of her body habitus and the extent of disease she was considered a poor surgical candidate, and endoscopic biliary decompression was chosen as the treatment of first intent.
Clinical & biological
Clinical: obese (BMI 38.8 kg/m²), marked jaundice, haemodynamically and respiratory stable.
Biological: severe cholestatic syndrome, with a total bilirubin of 26 mg/dL on admission.
Imaging
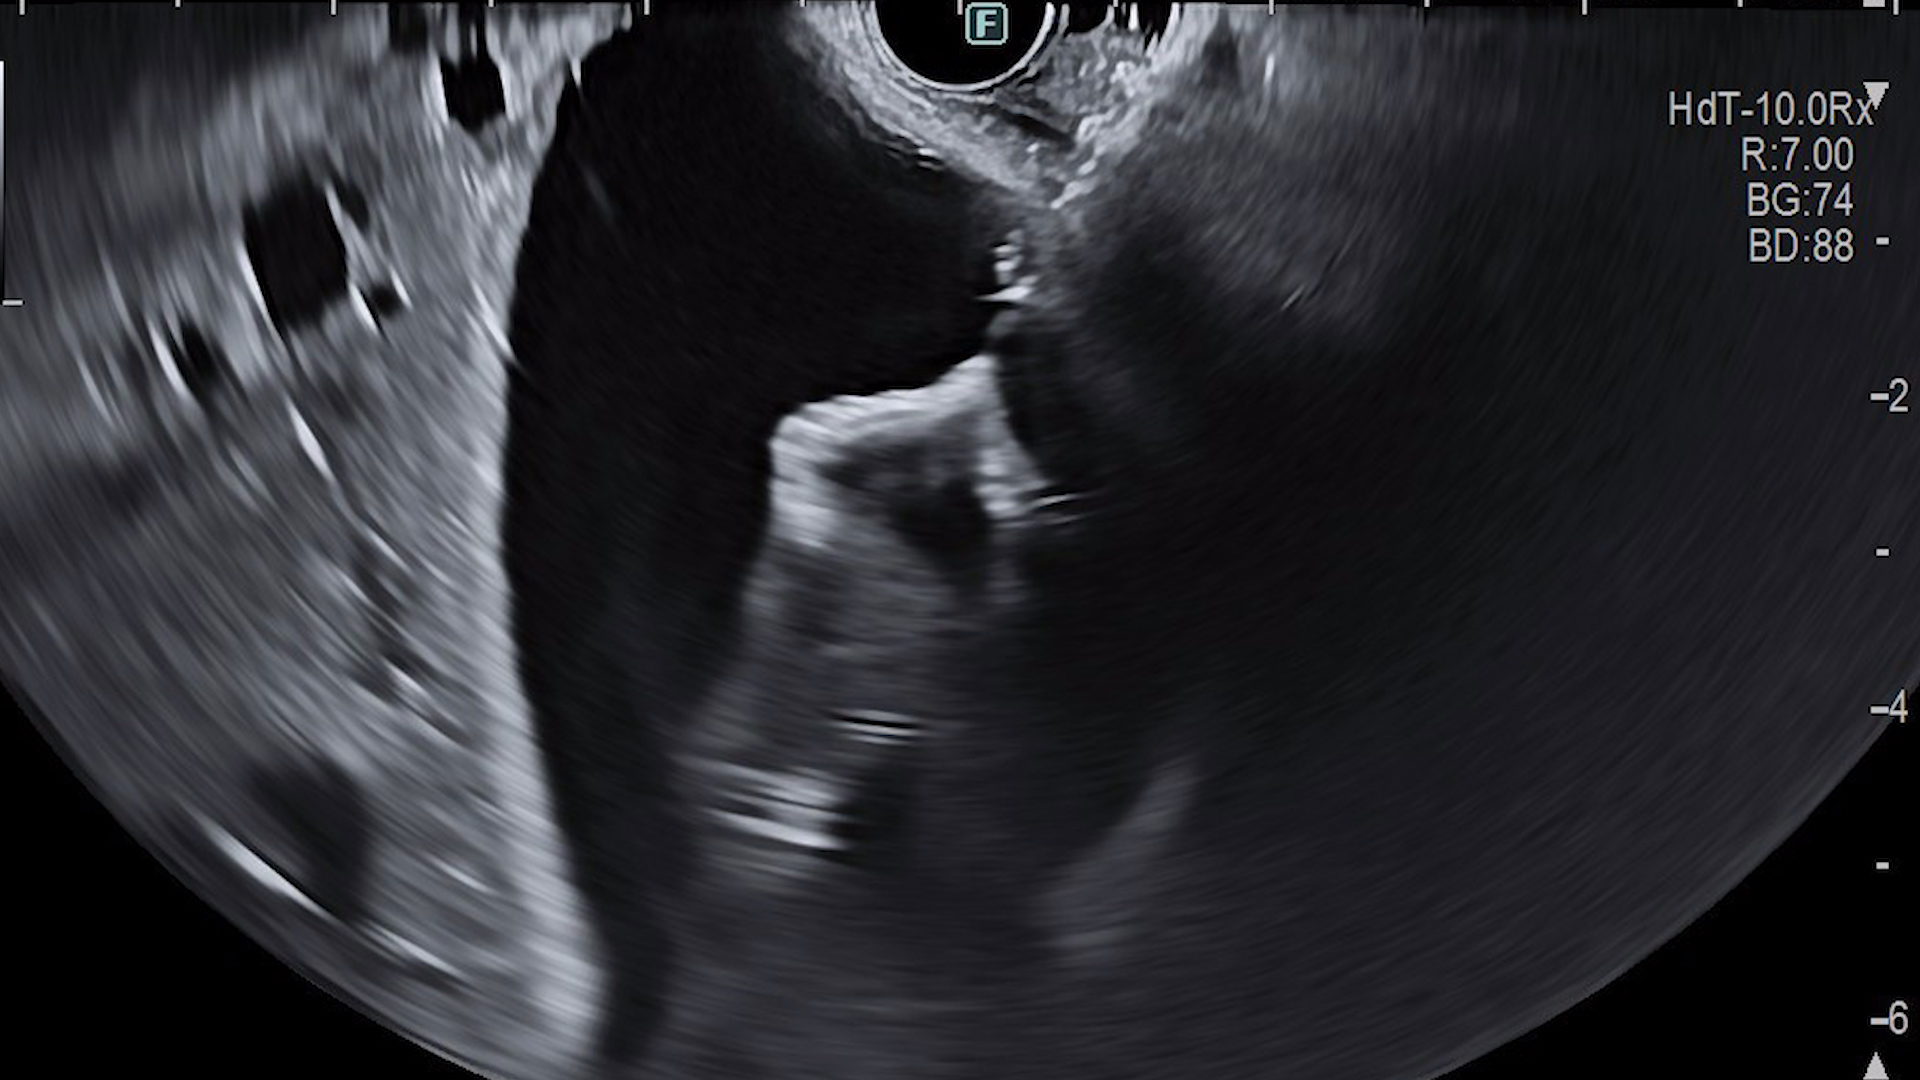
Endoscopic ultrasound demonstrated the distal biliary obstruction and the responsible lesion, which measured 3.37 cm (Figure 1). EUS-guided fine-needle biopsy (EUS-FNB) of the lesion established the diagnosis: adenocarcinoma with a biliopancreatic phenotype, consistent with distal cholangiocarcinoma.
Endoscopic management — a stepwise approach: ERCP was attempted first, as standard of care. Deep biliary cannulation failed despite repeated attempts. An EUS-guided rendezvous was then attempted. The extrahepatic bile duct was punctured transduodenally, but the guidewire could not be negotiated across the tight malignant stricture and into the duodenal lumen, so the rendezvous had to be abandoned.
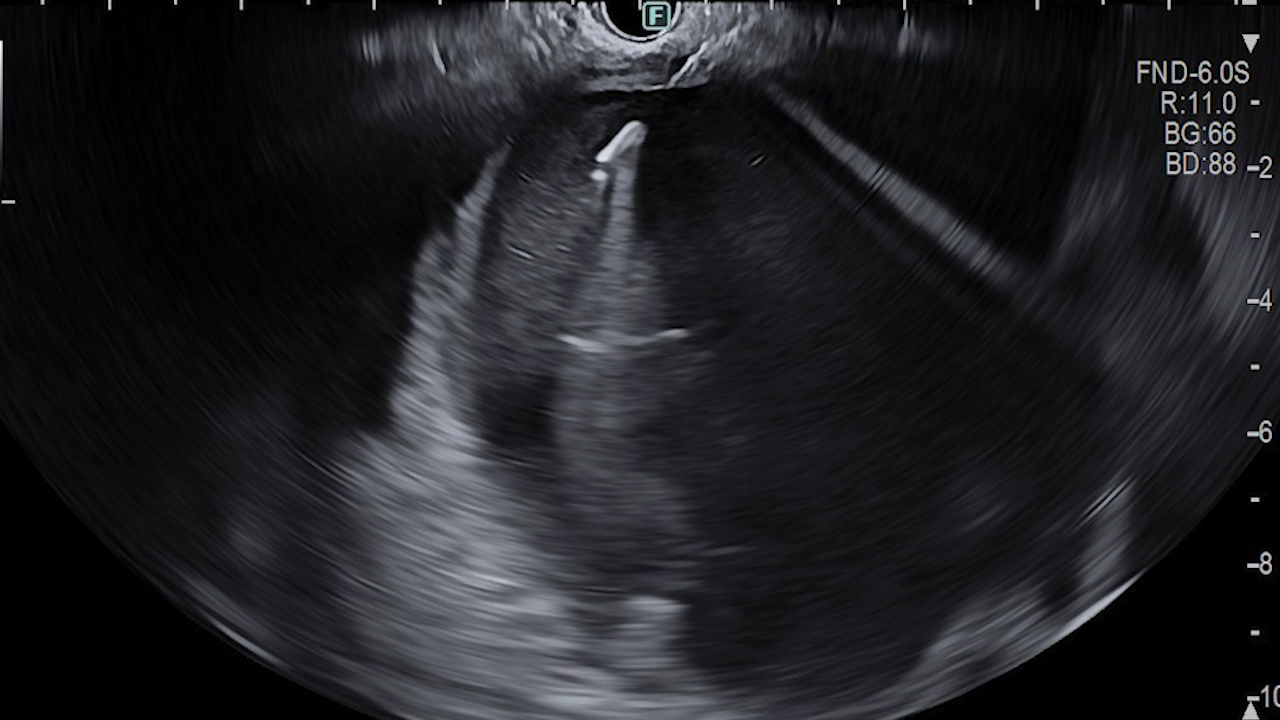
Salvage EUS-guided choledochoduodenostomy (EUS-CDS) was therefore performed in the same session. From the duodenal bulb the dilated extrahepatic bile duct was identified and the interposed vasculature was excluded by colour Doppler / E-Flow interrogation, defining a safe trajectory (Figure 2). The duct was punctured under real-time EUS guidance (Figure 3) and cholangiography was obtained, after which the guidewire was advanced and coiled deep into the intrahepatic biliary tree to secure the access (Figure 4). The choledochoduodenal fistula was created with a cystotome and a partially covered self-expandable metal stent (PC-SEMS) was deployed across the tract under combined endosonographic and fluoroscopic control (Figure 5). No lumen-apposing metal stent was used.
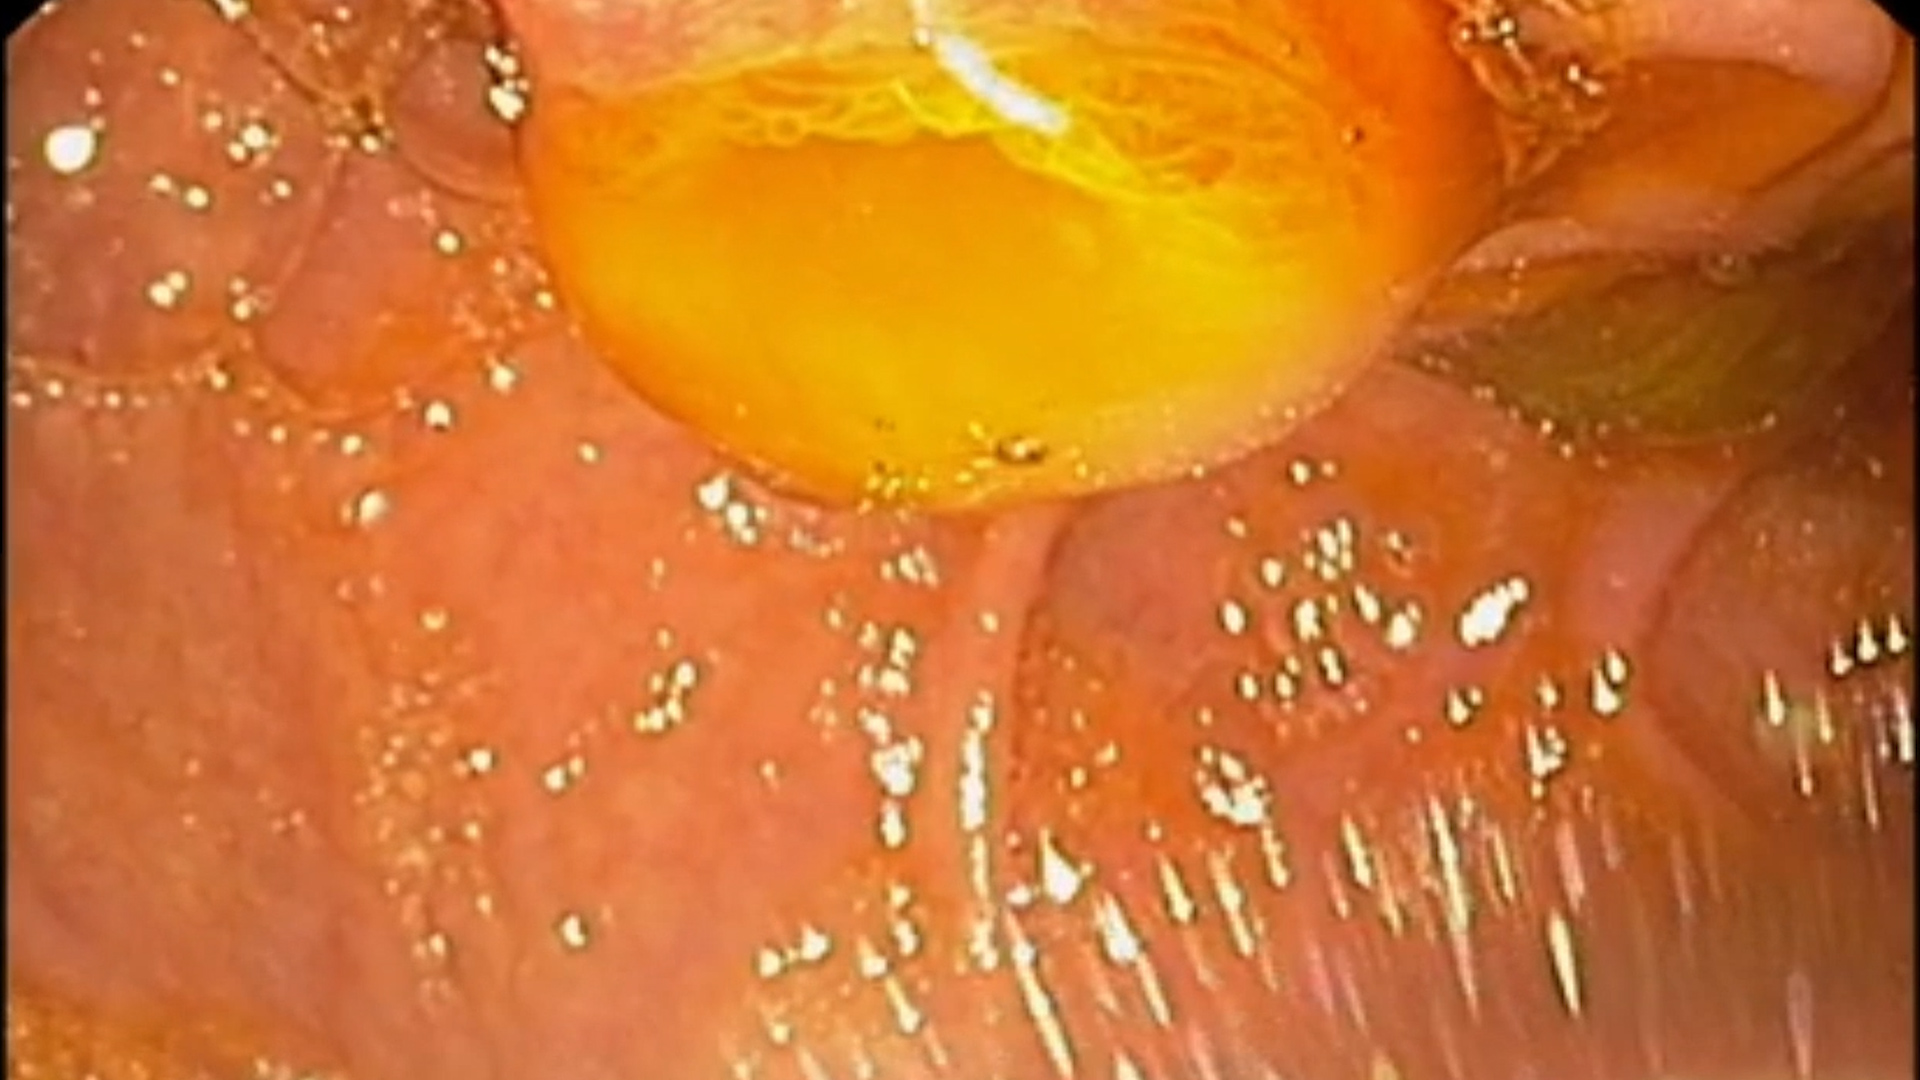
Outcome: Total bilirubin fell from 26 mg/dL to 6 mg/dL within 24 hours. Gastroscopy at 24 hours confirmed the correct position of the stent in the duodenal bulb with bile draining freely through it (Figure 6), and transabdominal ultrasound demonstrated bilobar aerobilia, confirming effective biliary decompression. The patient was discharged 48 hours after the procedure.
Figure legends:
Figure 1 – EUS assessment of the biliopancreatic region: the lesion responsible for the obstruction, measuring 3.37 cm, sampled by fine-needle biopsy.
Figure 2 – Colour Doppler (E-Flow) interrogation before puncture: the dilated extrahepatic bile duct with the adjacent vasculature mapped to define a safe transduodenal trajectory.
Figure 3 – EUS-guided transduodenal puncture of the dilated extrahepatic bile duct, with the needle tip within the ductal lumen.
Figure 4 – Cholangiography after transduodenal access, with the guidewire advanced and coiled deep into the intrahepatic biliary tree.
Figure 5 – Fluoroscopic control after deployment of the partially covered self-expandable metal stent across the choledochoduodenal fistula.
Figure 6 – Endoscopic control at 24 hours: correctly positioned stent in the duodenal bulb, with bile draining freely through it.
Diagnosis
Discussion
EUS-guided biliary drainage (EUS-BD) is now the preferred rescue after a failed ERCP in malignant distal biliary obstruction; ESGE recommends it over percutaneous transhepatic biliary drainage wherever the local expertise exists¹.
That recommendation rests on comparative data showing equivalent technical and clinical success but significantly fewer procedural and total adverse events for EUS-BD than for the percutaneous route², and, in a multicentre cohort, a far lower need for reintervention after EUS-choledochoduodenostomy than after percutaneous drainage (10.7% vs 77.6%)³.
The technique is no longer merely a bail-out: in the randomised DRA-MBO trial primary EUS-CDS matched ERCP for one-year stent patency (91.1% vs 88.1%) while achieving higher technical success (96.2% vs 76.3%) in a shorter procedural time⁴, and pooled first-line data show comparable success and safety for the two approaches⁵.
Two features of the present case deserve emphasis. First, the stepwise sequence — ERCP, then rendezvous, then transmural drainage — exhausts the least invasive options before a fistula is committed to; the rendezvous preserves transpapillary anatomy but depends on the guidewire crossing the stricture, and a tight malignant stricture is precisely where it fails.
Second, drainage was completed with a partially covered SEMS rather than a lumen-apposing metal stent. Published EUS-CDS cohorts include both stent types with comparable results³, and this case is a useful reminder that where electrocautery-enhanced LAMS are unavailable the procedure remains feasible with a cystotome-created fistula and a conventional metal stent.
Conclusions
A stepwise, multidisciplinary approach to malignant biliary obstruction in a poor surgical candidate: when both ERCP and EUS rendezvous fail, EUS-guided biliary drainage remains a safe and effective salvage option — even without lumen-apposing metal stents.
References
- van der Merwe SW, van Wanrooij RLJ, Bronswijk M, et al. Therapeutic endoscopic ultrasound: European Society of Gastrointestinal Endoscopy (ESGE) Guideline. Endoscopy. 2022;54(2):185-205. doi:10.1055/a-1717-1391
- Hayat U, Bakker C, Dirweesh A, et al. EUS-guided versus percutaneous transhepatic cholangiography biliary drainage for obstructed distal malignant biliary strictures in patients who have failed endoscopic retrograde cholangiopancreatography: a systematic review and meta-analysis. Endosc Ultrasound. 2022;11(1):4-16. doi:10.4103/EUS-D-21-00009
- Sawas T, Bailey NJ, Au Yeung KYK, et al. Comparison of EUS-guided choledochoduodenostomy and percutaneous drainage for distal biliary obstruction: a multicenter cohort study. Endosc Ultrasound. 2022;11(3):223-230. doi:10.4103/EUS-D-21-00031
- Teoh AYB, Napoleon B, Kunda R, et al. EUS-guided choledocho-duodenostomy using lumen apposing stent versus ERCP with covered metallic stents in patients with unresectable malignant distal biliary obstruction: a multicenter randomized controlled trial (DRA-MBO Trial). Gastroenterology. 2023;165(2):473-482.e2. doi:10.1053/j.gastro.2023.04.016
- Han SY, Kim SO, So H, et al. EUS-guided biliary drainage versus ERCP for first-line palliation of malignant distal biliary obstruction: a systematic review and meta-analysis. Sci Rep. 2019;9(1):16551. doi:10.1038/s41598-019-52993-x